Wearables and health
What if I walk more and sleep earlier? Google turns wearable data into 12-week body simulations
On November 11 Google Research introduced a coachable health age (CHA) framework with a companion study: the metric never guesses your birth year — it is built only from signals daily behavior can move, namely resting heart rate, step count, sleep duration and weekly Active Zone Minutes, optionally plus VO2max, sleep-regularity and insulin-resistance markers. Across 22,748 All of Us participants followed for more than 68,000 person-years, healthy people whose health age ran older than their calendar age at baseline were significantly more likely to develop hypertension, cardiovascular disease or type 2 diabetes over the next eight years, and adding CHA to age-sex-BMI baselines improved risk prediction most for adults under 50. The core piece is SensorWM, a world model pretrained on 2.28 million person-weeks from roughly 100,000 Fitbit users: given a two-week baseline it rolls out how 20 physiological markers would evolve over the next 12 weeks under different habit plans (average R² 0.664 versus 0.513 for TimesFM); a feasibility-constrained optimizer picks one of 125 candidate plans per person, and a language-model coach turns the simulation into a 12-week program — in blinded review, five certified lifestyle coaches and five board-certified physicians compared 49 profiles across 490 paired reviews, preferring the counterfactual-grounded plans 71.4% of the time and rating 99.2% of them safe on exercise intensity. The boundaries read clearly: investigational research prototypes, not clinical diagnostic tools, all from Google's own retrospective cohorts, with no prospective trial yet.
This account draws on Google Research's official post "Using wearables to enable cardiovascular-kidney-metabolic (CKM) risk profiling for personalized coaching" (page dated November 11, 2026; read in full by this site on November 12) and the preprint it links (arXiv:2611.08568, submitted November 5); the three figures in the body are the blog's own images. Every number is the Google team's self-reported caliber: this site took no part in the research and verified no raw data. It is the next link in the same chain as our November 9 piece on cuffless hypertension screening — that one asked whether a watch can detect it, this one asks what changing your habits could do about it.
After detection: this line adds "what can I change"
The usual endpoint of smartwatch health research is detection: finding hypertension cues in waveforms — our November 9 piece on cuffless screening was exactly that — or surfacing atrial fibrillation from heart rate. This work, published by Google on November 11, moves the endpoint one step further: from spotting risk to answering "what happens to my body if I change my habits?" The official blog phrases it the way a reader would: how do my recent habits shape my heart-kidney-metabolic health right now, and if I sleep 30 minutes longer or add a brisk walk, how much better could things get in three months?
The framework has three layers: a coachable health age (CHA) gives your current state an interpretable coordinate; the SensorWM world model simulates the what-if; a language-model coach turns the simulation into a 12-week plan. A companion study adds three routine blood draws and splits the health age across the cardiovascular, kidney and metabolic systems. Keep the dates apart: the preprint hit arXiv on November 5, 2026, and the official post is dated November 11; both studies self-describe as investigational research prototypes — not product features, and not diagnostic tools.
How this connects to our earlier piece: November 9's "65.8% vs 55.3%" sits on the same watch-to-health line and answers detection — whether a person is in a persistently hypertensive state, validated against 24-hour ambulatory monitoring. Today's research measures no blood pressure at all; it asks about intervention — simulate the futures that behavior change could produce, then hand over a plan. The two cannot substitute for each other: detection is the starting point, and change is the question that follows. This piece picks up the second half.
Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
A coachable health age, built only from what can change
Plenty of "biological age" models use blood markers or epigenetic clocks to guess your birth year. The paper argues that road has two flaws: such models latch onto traits you cannot easily change, and as black boxes they cannot say what changing one habit would do. CHA's design principle runs the other way — every input must be something daily choices can keep moving: resting heart rate, daily steps, sleep duration, weekly Active Zone Minutes, plus VO2max, sleep regularity and insulin resistance when available. Overlap between signals is mathematically adjusted away so each habit contributes its own share of the health-age delta (CHA minus calendar age): a delta of −3 years means your physiological profile reads younger than your calendar age; a positive delta means accelerated aging.
Three independent validations. First, All of Us, 22,748 participants and more than 68,000 person-years: healthy participants whose health age ran older than their calendar age at baseline were significantly more likely to develop hypertension, cardiovascular disease or type 2 diabetes over the following eight years; adding CHA to an age-sex-BMI baseline significantly improved risk discrimination, most of all for adults under 50 — the official figure shows the C-index moving 0.6485 to 0.6541. Second, a longitudinal Fitbit cohort of 1,464 people: across two years of consecutive three-month windows, CHA fell for those who sustained a habit change. Third, the WEAR-ME cohort: CHA aligned with the modified Life's Essential 8 cardiovascular score, metabolic-syndrome severity and participants' self-reported health, while clocks trained to guess birth year did not.
Panel b of the official figure holds one more detail worth reading: incident type 2 diabetes came with a mean baseline delta of +0.37 years and incident cardiovascular disease +0.23 — small numbers, but directionally consistent with confidence intervals off zero. Health age is not a frightening line on a lab report; it is a slowly drifting coordinate, which is exactly why "can it be moved" matters more as a design core than raw precision — the point of a coordinate is watching it move.

Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
- Preprint: Personalized health coaching via coachable health age and counterfactual wearable trajectories (arXiv:2611.08568)Preprint · submitted November 5, 2026 · abstract page read November 12Abstract page read. Authors Simon A. Lee, Zeinab Esmaeilpour, Menglian Zhou et al., 20 in total, with Ahmed A. Metwally as the last author; q-bio.QM cross-listed cs.LG. Abstract caliber: WEAR-ME N=2,780, All of Us N=22,748, longitudinal Fitbit N=1,464; pretraining on "over 2.2 million person-weeks from approximately 100,000 participants"; SensorWM averages R² 0.664 for multi-week physiological response prediction; blinded review 71.4% (overall quality) and 71.0% (adherence), both p<0.001; board-certified clinicians judged 99.2% of counterfactual plans safe versus 97.6% for comparison plans — matching the official figure's safety panel (243/245 vs 239/245). Code is slated to open on the Google Health GitHub upon publication.
SensorWM: a what-if simulator for the body
Knowing where you stand is not knowing where you can go. Turning a health age into a plan means answering a counterfactual question: over the next 12 weeks, how would my markers move if steps, sleep and cardio changed this way or that way? Plugging new targets into a static calculator cannot capture it — the body is a connected system: keep moving more and sleeping better for several weeks and resting heart rate and heart-rate variability improve too, compounding the benefit downstream. Hence the name SensorWM: a world model, but for the body.
The pretraining corpus is 2.28 million person-weeks of de-identified data from roughly 100,000 consenting Fitbit users. Given a two-week baseline, it rolls out how 20 physiological markers would evolve over the next 12 weeks under different habit plans, averaging R² 0.664 — against baselines the official figure lists as TimesFM 0.513, last-observation-carried-forward 0.503, the 4-week mean 0.413 and the 2-week mean 0.077 — while preserving the clinical patterns tied to diabetes, hypertension and insulin resistance. In other words, it does not learn how people on average behave; it learns what this person's markers do under a given course of action.
After simulation comes selection: 125 candidate 12-week plans per person, each compared against a status-quo rollout; a feasibility-constrained optimizer trades projected benefit against each person's historical habit flexibility and clinical safety bounds. The official figure's example is blunt: for a high-adherence user the max simulated reduction is −2.9 years and the chosen plan −2.3; for a low-adherence user the max is −6.7 but the chosen plan just −1.3 — the most aggressive program is worth nothing if you quit in week two. A language-model coach then turns the top-ranked path into a progressive, executable 12-week program.

Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
- Preprint: Personalized health coaching via coachable health age and counterfactual wearable trajectories (arXiv:2611.08568)Preprint · submitted November 5, 2026 · abstract page read November 12Abstract page read. Authors Simon A. Lee, Zeinab Esmaeilpour, Menglian Zhou et al., 20 in total, with Ahmed A. Metwally as the last author; q-bio.QM cross-listed cs.LG. Abstract caliber: WEAR-ME N=2,780, All of Us N=22,748, longitudinal Fitbit N=1,464; pretraining on "over 2.2 million person-weeks from approximately 100,000 participants"; SensorWM averages R² 0.664 for multi-week physiological response prediction; blinded review 71.4% (overall quality) and 71.0% (adherence), both p<0.001; board-certified clinicians judged 99.2% of counterfactual plans safe versus 97.6% for comparison plans — matching the official figure's safety panel (243/245 vs 239/245). Code is slated to open on the Google Health GitHub upon publication.
Blinded review: 71.4% pick it best, 99.2% rated safe
The pivotal question: does grounding a language model in world-model simulations actually beat handing the same wearable history to the same model? The design: five certified lifestyle coaches and five board-certified physicians (primary care and lifestyle medicine) reviewed 49 participant profiles across five behavioral personas in 490 paired, blinded comparisons, with automated evaluation across the full 2,780-person WEAR-ME cohort. The results: counterfactual-grounded plans were chosen best overall in 71.4% of evaluations (p<0.001) and rated more likely to drive long-term adherence in 71.0% (p<0.001); physicians found 99.2% of counterfactual plans within safe exercise-intensity limits versus 97.6% for the generic comparison plans (the official figure's panel e caliber: 243/245 versus 239/245), and judged 97.6% of physiological claims accurate.
Why did it work? The reviewers converged on one answer: showing the status-quo trajectory next to achievable what-if options. Clinicians preferred the side-by-side contrast 92% to 8%, and 97% versus 59% said it gave a clear reason to act and a stronger sense of agency. The numbers themselves are old friends — steps, sleep, cardio; what is new is the presentation: a concrete, personal, simulated what-if.
The boundary, stated plainly: the experts rated plan quality and safety, not health outcomes; the 490 comparisons measure paired preference, not clinical efficacy. "Better" here means "more likely to be adopted, less likely to cross safety lines" — one validation short of "more likely to improve health," which is precisely why the authors name prospective trials as the next step.
Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
- Preprint: Personalized health coaching via coachable health age and counterfactual wearable trajectories (arXiv:2611.08568)Preprint · submitted November 5, 2026 · abstract page read November 12Abstract page read. Authors Simon A. Lee, Zeinab Esmaeilpour, Menglian Zhou et al., 20 in total, with Ahmed A. Metwally as the last author; q-bio.QM cross-listed cs.LG. Abstract caliber: WEAR-ME N=2,780, All of Us N=22,748, longitudinal Fitbit N=1,464; pretraining on "over 2.2 million person-weeks from approximately 100,000 participants"; SensorWM averages R² 0.664 for multi-week physiological response prediction; blinded review 71.4% (overall quality) and 71.0% (adherence), both p<0.001; board-certified clinicians judged 99.2% of counterfactual plans safe versus 97.6% for comparison plans — matching the official figure's safety panel (243/245 vs 239/245). Code is slated to open on the Google Health GitHub upon publication.
Adding three routine blood draws: a health age per organ
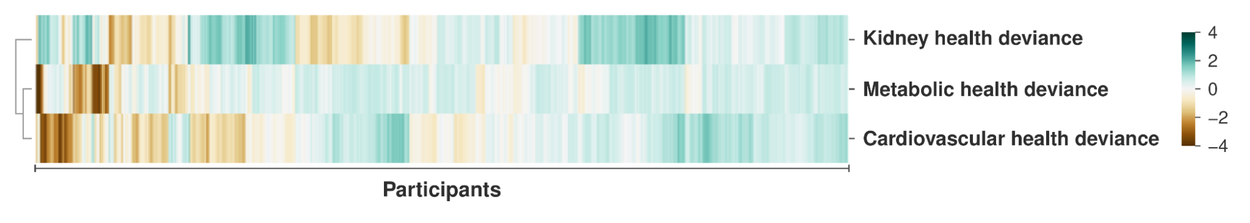
CHA is modular: when routine labs exist, the framework can join the continuous wearable streams to occasional blood markers. The companion study, "Cardiovascular-Kidney-Metabolic Health Age Using Wearables and Blood Biomarkers", splits the health age across the heart, kidney and metabolic systems for 819 WEAR-ME participants: wearable signals (resting heart rate, steps, active zone minutes, sleep) plus three routine blood markers — cholesterol-to-HDL ratio (cardiovascular), estimated glomerular filtration rate (kidney) and the HOMA-IR insulin-resistance index (metabolic). Each marker becomes a normalized deviance score measuring its distance from healthy clinical thresholds.
The most instructive finding: multi-organ aging does not follow a single template. Metabolic and cardiovascular strain tend to be correlated, but early kidney decline frequently shows up independently — in the heatmap, the kidney's dark bands often occupy a column alone. That matches the clinical story of CKM syndrome progressing silently for years: occasional clinic draws cannot see day-to-day lifestyle, continuous wearables cannot see blood chemistry, and only together do they show which system is drifting first. The CKM health-age gap aligned with objective clinical scores (modified Life's Essential 8 r=−0.58; metabolic-syndrome severity r=0.65) and with how healthy participants felt day to day.
Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
Boundaries and what is worth waiting for
Every number shares one caliber: Google's own team, its own retrospective cohorts, offline evaluation. The post is explicit about the nature — these models are "investigational research prototypes rather than clinical diagnostic tools"; the evaluations ran on retrospective research cohorts, and no prospective trial has yet tested whether interactive what-if coaching helps people build lasting habits and improve long-term health. This site took no part in the research, reproduced no numbers, and has read no third-party replication; the Fitbit data, expert panels and evaluation procedures all come from the publisher's description.
Set beside the November 9 screening study, the shape of this line comes into focus: screening asks whether something is there, risk profiling asks where the drift is, counterfactual simulation asks what change would do, and the coaching plan asks where to start. Each step carries its own evidence, but the loop they form together has not yet been validated in a real population. Worth waiting for: prospective-trial results, SensorWM generalizing to third-party data, and which product form — under what review process — carries these capabilities onto consumer watches. That last jump, from research into life, is the one this site watches for.
- Read Google Research's original postPage dated November 11, 2026; source of all three official figures and every claim.
- Read the preprint abstract (arXiv:2611.08568)Submitted November 5, 2026; R² 0.664, the three cohorts and the blinded-review numbers are in the abstract.
- Read our earlier piece: cuffless hypertension screeningPublished November 9, 2026; the detection link on the same watch-to-health line.
Sources and further reading
- Google Research's official post: Using wearables to enable CKM risk profiling for personalized coachingOfficial blog · page dated November 11, 2026 · read in full November 12Read in full. Checked the key claims: CHA uses only modifiable signals (resting heart rate, steps, sleep duration, weekly Active Zone Minutes; optional VO2max, sleep regularity, insulin resistance); three validations — All of Us 22,748 participants over 68,000 person-years (largest gains under 50), a longitudinal Fitbit cohort of 1,464 (CHA fell for those with sustained habit change), and WEAR-ME alignment with Life's Essential 8 and metabolic-syndrome scores; SensorWM pretrained on 2.28M person-weeks from ~100k Fitbit users, forecasting 20 markers over 12 weeks from a two-week baseline, beating TimesFM; 125 candidate plans per person with feasibility-constrained optimization (example −2.3y vs −1.3y); blinded review by 5 certified lifestyle coaches and 5 board-certified physicians over 49 profiles, 5 personas, 490 paired reviews — counterfactual plans chosen best 71.4% (p<0.001) and more likely to stick 71.0% (p<0.001), physicians rated 99.2% within safe intensity limits and 97.6% accurate on physiological claims, with the status-quo contrast preferred 92% to 8% and agency 97% to 59%; the companion study adds cholesterol/HDL ratio, eGFR and HOMA-IR for 819 WEAR-ME participants, finding metabolic and cardiovascular strain correlated while early kidney decline often appears independently (r=−0.58 and 0.65). The post states plainly: offline retrospective evaluation, investigational research prototypes, not clinical diagnostic tools. Acknowledgements include Esmaeilpour, Lee, Zhou, Poh, McDuff, Metwally and others.
- Preprint: Personalized health coaching via coachable health age and counterfactual wearable trajectories (arXiv:2611.08568)Preprint · submitted November 5, 2026 · abstract page read November 12Abstract page read. Authors Simon A. Lee, Zeinab Esmaeilpour, Menglian Zhou et al., 20 in total, with Ahmed A. Metwally as the last author; q-bio.QM cross-listed cs.LG. Abstract caliber: WEAR-ME N=2,780, All of Us N=22,748, longitudinal Fitbit N=1,464; pretraining on "over 2.2 million person-weeks from approximately 100,000 participants"; SensorWM averages R² 0.664 for multi-week physiological response prediction; blinded review 71.4% (overall quality) and 71.0% (adherence), both p<0.001; board-certified clinicians judged 99.2% of counterfactual plans safe versus 97.6% for comparison plans — matching the official figure's safety panel (243/245 vs 239/245). Code is slated to open on the Google Health GitHub upon publication.